
Iron deficiency remains the single most prevalent nutritional deficiency on the planet, affecting an estimated 2 billion people and causing iron deficiency anemia in roughly 25% of the global population [4] [15]. For menstruating women, vegetarians, athletes, and pregnant individuals, the risk climbs even higher — yet many people supplement incorrectly, choose the wrong form, or never get tested in the first place.
The challenge with iron is its dual nature: absolutely essential for oxygen transport, energy production, and cognitive function, yet potentially toxic when taken in excess. Unlike most minerals, the human body has no active mechanism to excrete iron — making proper testing, form selection, and dosing critical. [5] [7]
This guide breaks down everything you need to know about iron supplementation — from understanding your lab results and choosing between ferrous sulfate, bisglycinate, and other forms, to optimizing absorption with vitamin C and avoiding common mistakes that sabotage your progress. [9] [14]
This content is for informational purposes only and does not constitute medical advice. Always consult a qualified healthcare provider before starting any supplement regimen, especially iron, which requires testing before use.
What Is Iron and Why Is It Essential for Your Health?
Iron is an essential trace mineral that your body cannot produce on its own — you must obtain it through diet or supplementation. It serves as the core component of hemoglobin, the protein in red blood cells responsible for transporting oxygen from your lungs to every tissue in your body. Adults carry approximately 3–4 grams of total body iron, with about 65% in hemoglobin, 25% in storage proteins (ferritin and hemosiderin), and 10% in muscle myoglobin.
Dietary iron comes in two forms: heme iron from animal sources (meat, poultry, fish) with 15–35% absorption, and non-heme iron from plant sources and supplements with just 2–20% absorption [12]. This dramatic difference in bioavailability is why vegetarians and vegans need approximately 1.8 times more dietary iron than meat-eaters [8]. The body tightly regulates iron absorption through hepcidin, a liver hormone that acts as the master iron regulator — increasing when stores are adequate and decreasing when the body needs more iron.
What Are the Two Types of Dietary Iron?
Heme iron is bound to hemoglobin and myoglobin in animal tissues and absorbs at 15–35% regardless of other dietary factors.
Non-heme iron is the free form found in plants, fortified foods, and all supplements — it absorbs at just 2–20% and is heavily influenced by enhancers (vitamin C) and inhibitors (calcium, tannins, phytates). All oral iron supplements deliver non-heme iron, which is why absorption optimization matters so much [11] [18] [20].
How Is Iron Distributed in Your Body?
Your body distributes iron across four major compartments: hemoglobin (65%) in red blood cells for oxygen transport, ferritin and hemosiderin (25%) as storage in the liver, spleen, and bone marrow, myoglobin (10%) in muscles for local oxygen storage, and enzymes (<1%) for metabolic functions including DNA synthesis, detoxification, and energy production. The body efficiently recycles approximately 90% of iron from old red blood cells through a process managed by macrophages in the spleen.

Are You Unknowingly Inflaming Your Body?
Get the free Health Vitals & Nutrient Checklist — the daily guide that shows you which habits and supplements are silently triggering inflammation.
How Does Iron Work in Your Body?
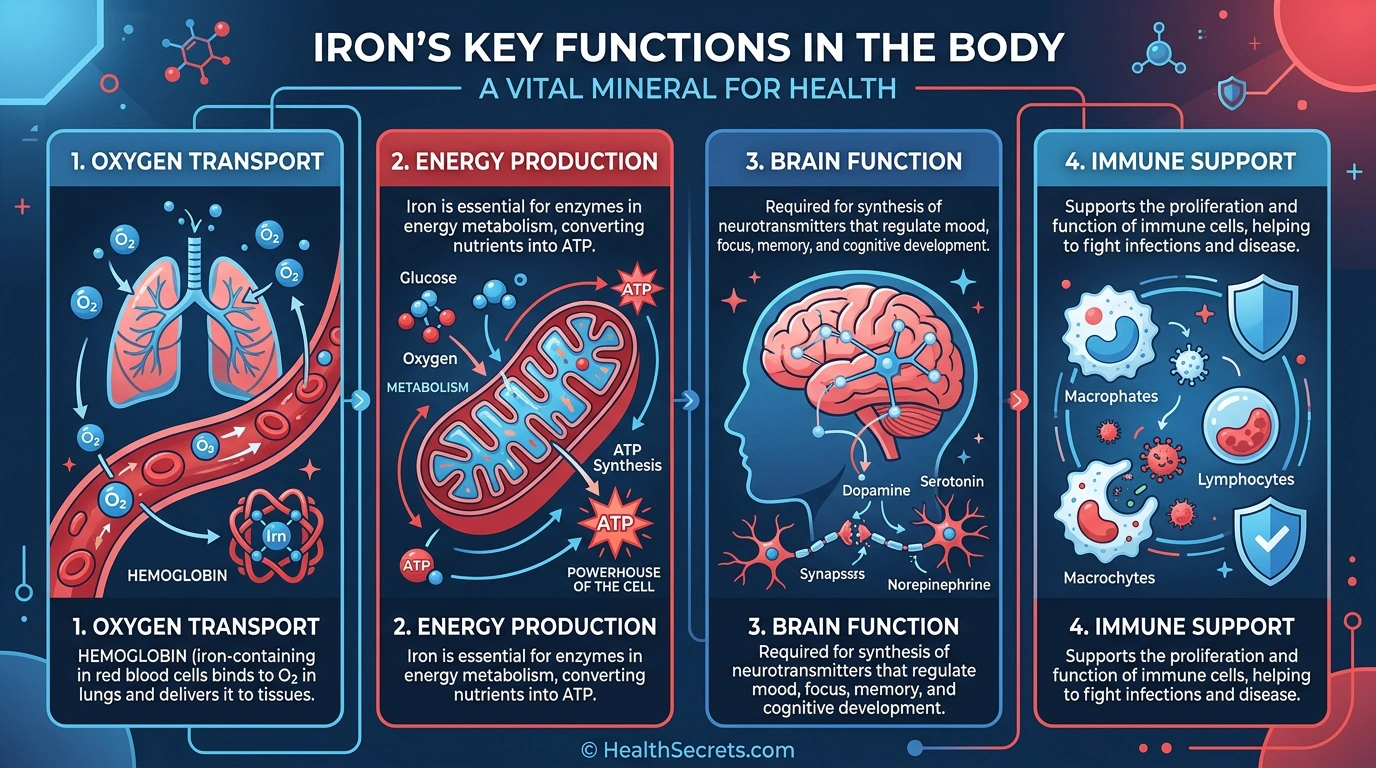
Iron performs several critical biological functions beyond oxygen transport. Understanding these mechanisms explains why even mild deficiency — before anemia develops — can cause fatigue, brain fog, and impaired immunity. Iron's roles span from cellular energy production to neurotransmitter synthesis.
How Does Iron Transport Oxygen Throughout Your Body?
Iron sits at the center of hemoglobin's heme group, where it binds oxygen molecules in the lungs and releases them in tissues. Each hemoglobin molecule contains four iron atoms, enabling each red blood cell to carry approximately 1 billion oxygen molecules. When iron stores drop, hemoglobin production decreases, oxygen delivery becomes inefficient, and tissues experience hypoxia — manifesting as fatigue, shortness of breath, and exercise intolerance. Myoglobin, a related iron-containing protein in muscle cells, stores oxygen locally for immediate use during physical activity.
Why Does Iron Deficiency Cause Fatigue Even Without Anemia?
Iron is a required cofactor in the mitochondrial electron transport chain, specifically in cytochrome enzymes that produce ATP — your body's primary energy currency. Research published in the American Journal of Clinical Nutrition demonstrated that iron supplementation significantly improved fatigue scores and quality of life in iron-deficient women who were not yet anemic, confirming that depleted iron stores impair energy production before hemoglobin drops below the anemia threshold.
How Does Iron Affect Brain Function and Mood?
Iron is essential for synthesizing dopamine, serotonin, and norepinephrine — neurotransmitters that regulate mood, motivation, and cognitive performance. It also supports myelin formation, the insulating sheath around nerve fibers that enables rapid signal transmission. Studies in adolescents have shown that iron supplementation improved memory, attention, and learning capacity in those with low ferritin levels. Iron deficiency during infancy and early childhood can cause irreversible cognitive developmental delays.
Does Iron Support Immune Function?
Iron is required for the proliferation and maturation of immune cells, particularly lymphocytes and neutrophils. However, iron regulation in immunity involves a delicate balance — while deficiency impairs immune response and increases infection susceptibility, excess iron can actually feed pathogenic bacteria and parasites. This is why the body sequesters iron during acute infections through hepcidin upregulation, a process called "nutritional immunity."

Evidence-Based Supplement Organizer & Safety Log
Track your daily intake, verify third-party certifications, and prepare clear questions for your clinician.
How Well Are Different Iron Supplements Absorbed?
Iron supplement absorption varies dramatically depending on the chemical form, what you take it with, and your current iron status. Choosing the right form and optimizing absorption conditions can mean the difference between effective repletion and months of frustration with no improvement.
Ferrous vs. ferric forms: Ferrous (Fe²⁺) iron is significantly better absorbed than ferric (Fe³⁺) iron because the intestinal transporter DMT1 preferentially absorbs the ferrous form. Ferric iron must first be reduced to ferrous iron by stomach acid and duodenal cytochrome b before absorption — an extra step that reduces bioavailability.
| Form | Elemental Iron | Absorption | GI Tolerance | Best For |
|---|---|---|---|---|
| Ferrous Sulfate | 20% (65 mg/325 mg) | Good | Poor | Budget, severe deficiency |
| Ferrous Bisglycinate | ~20% (25–50 mg/cap) | Excellent | Excellent | GI sensitivity, first choice |
| Ferrous Fumarate | 33% (106 mg/325 mg) | Good | Poor–Moderate | High elemental iron needs |
| Ferrous Gluconate | 12% (38 mg/325 mg) | Good | Moderate | Moderate deficiency |
| Carbonyl Iron | ~99% pure | Moderate (slow) | Good | Safety-focused, children |
Ferrous bisglycinate deserves special attention: a randomized trial published in the Journal of Perinatal Medicine found that 25 mg of iron as bisglycinate was as effective as 50 mg of ferrous sulfate for preventing iron deficiency during pregnancy, with significantly fewer GI complaints (P=0.001) [2]. The chelated glycine molecules protect iron through the stomach and enhance absorption through a separate amino acid transport pathway.
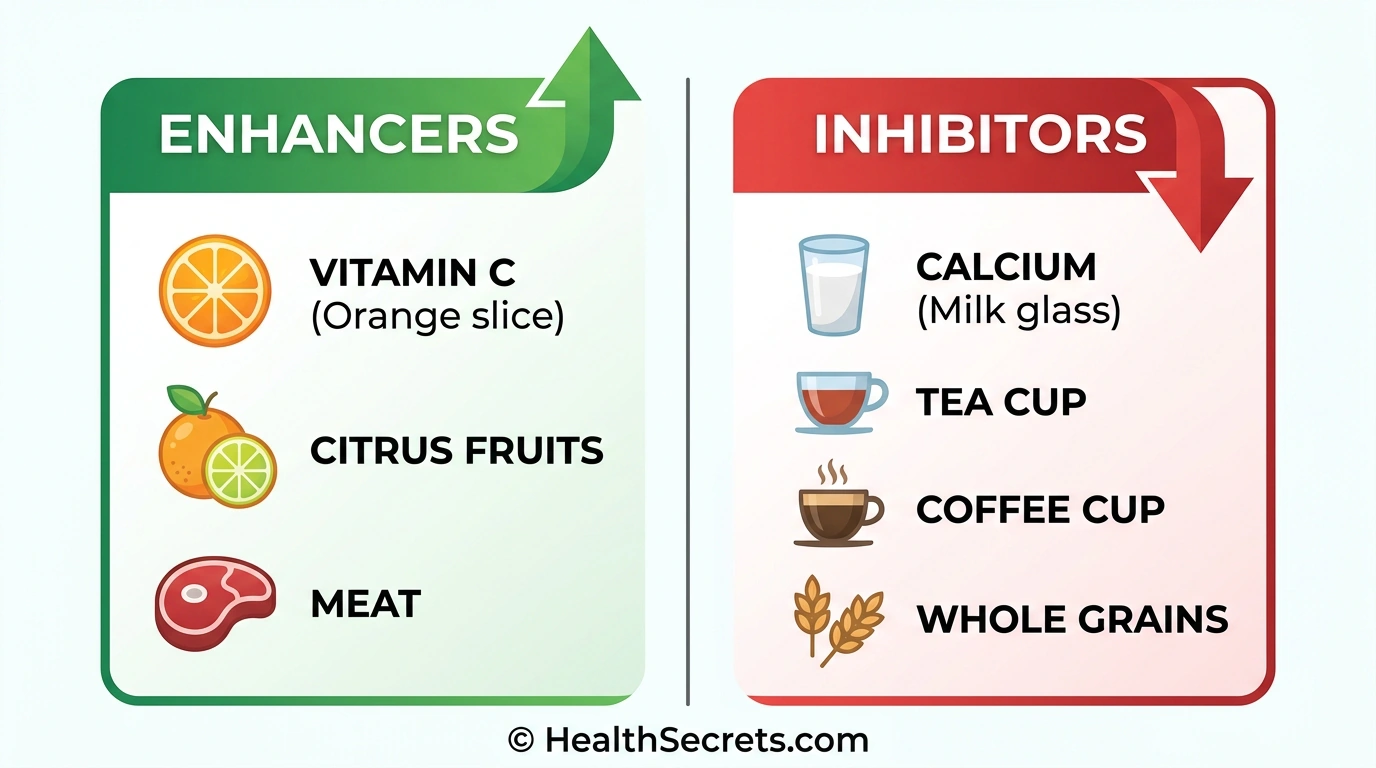
Key absorption enhancers and inhibitors:
- Vitamin C (ascorbic acid): The most powerful enhancer — increases non-heme iron absorption 3–4x by reducing Fe³⁺ to Fe²⁺ and forming soluble chelates. Take 100–200 mg with your iron supplement.
- Calcium: Strongly inhibits absorption. Separate dairy and calcium supplements by at least 2 hours.
- Tannins (tea and coffee): Can reduce absorption by 50–90%. Avoid within 1–2 hours of iron.
- Phytates: Found in whole grains, legumes, and nuts. Soaking and sprouting reduces phytate content.
- PPIs and antacids: Reduce stomach acid needed for iron absorption. Separate by 2–4 hours.
Alternate-day dosing: Groundbreaking research from ETH Zurich demonstrated that iron absorption was significantly higher (+33%) with alternate-day dosing compared to consecutive-day dosing [3]. Oral iron triggers a hepcidin spike that persists for 24 hours, temporarily blocking further absorption. This finding suggests that taking iron every other day may be more effective than daily dosing for many people.

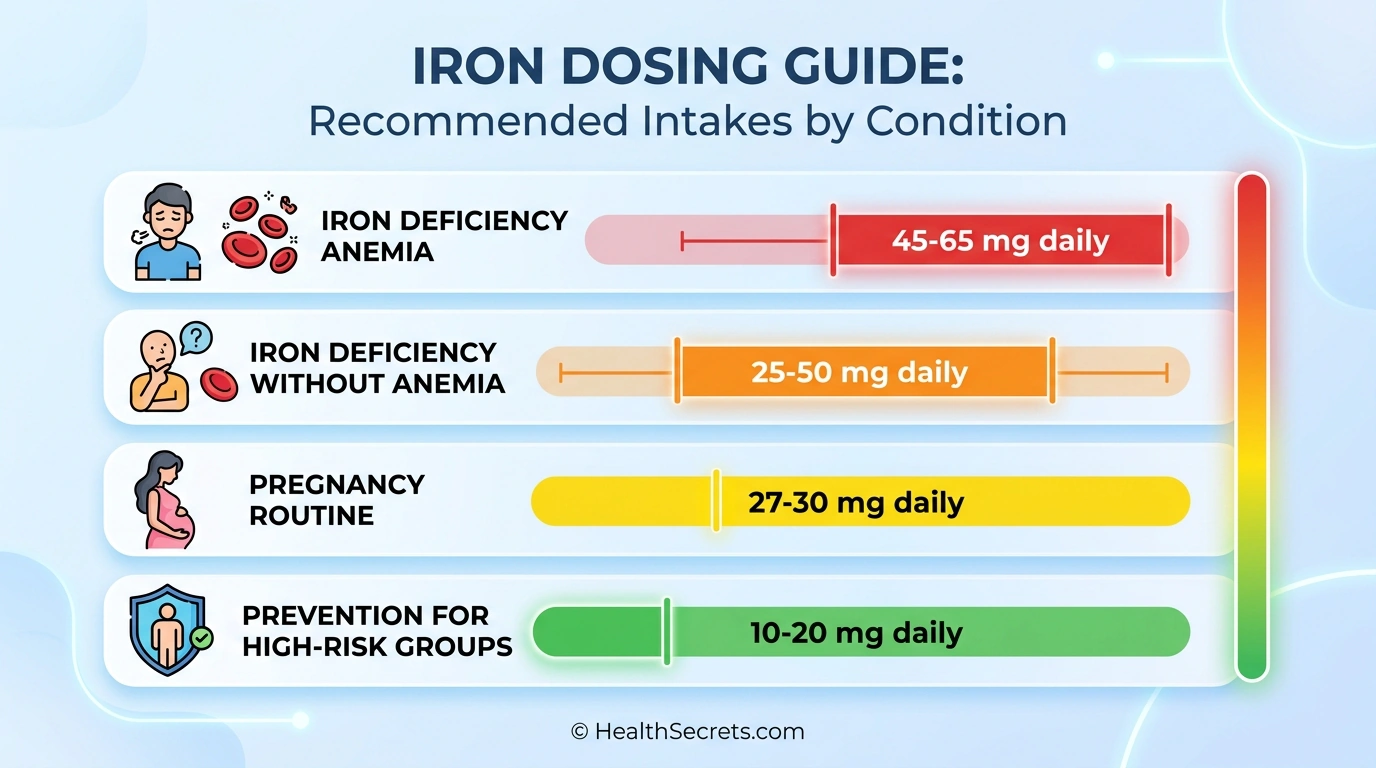
How Much Iron Should You Take Daily?
Iron dosing depends on your current status, the reason for supplementation, and which form you choose. The critical distinction is between elemental iron (the actual iron your body absorbs) and total compound weight — a 325 mg ferrous sulfate tablet contains only 65 mg of elemental iron. Always dose based on elemental iron content.
| Condition | Elemental Iron | Duration | Preferred Form |
|---|---|---|---|
| Iron deficiency (no anemia) | 25–50 mg/day | 3–6 months, retest | Bisglycinate [19] |
| Iron deficiency anemia | 45–65 mg/day | 3–6 months minimum | Sulfate or bisglycinate |
| Pregnancy (routine) | 27–30 mg/day | Throughout pregnancy | Bisglycinate preferred |
| Pregnancy (anemic) | 60–120 mg/day | Medical supervision | Bisglycinate or sulfate |
| Prevention (high-risk) | 10–20 mg/day | Ongoing while at risk | Low-dose bisglycinate |
| Important dosing principles: |
- Start low, go slow: Begin with a lower dose and increase as tolerated to minimize GI side effects
- Divide large doses: If taking >65 mg elemental iron, split into two doses for better absorption and fewer side effects [10]
- Empty stomach vs. with food: Empty stomach maximizes absorption (2–3x better) but causes more GI upset. Take with a small, low-calcium meal if intolerant
- Tolerable Upper Intake Level: 45 mg elemental iron/day from supplements. Therapeutic doses for anemia exceed this and require medical supervision
- Retest at 3 months: Check ferritin and hemoglobin to assess progress and adjust dosing
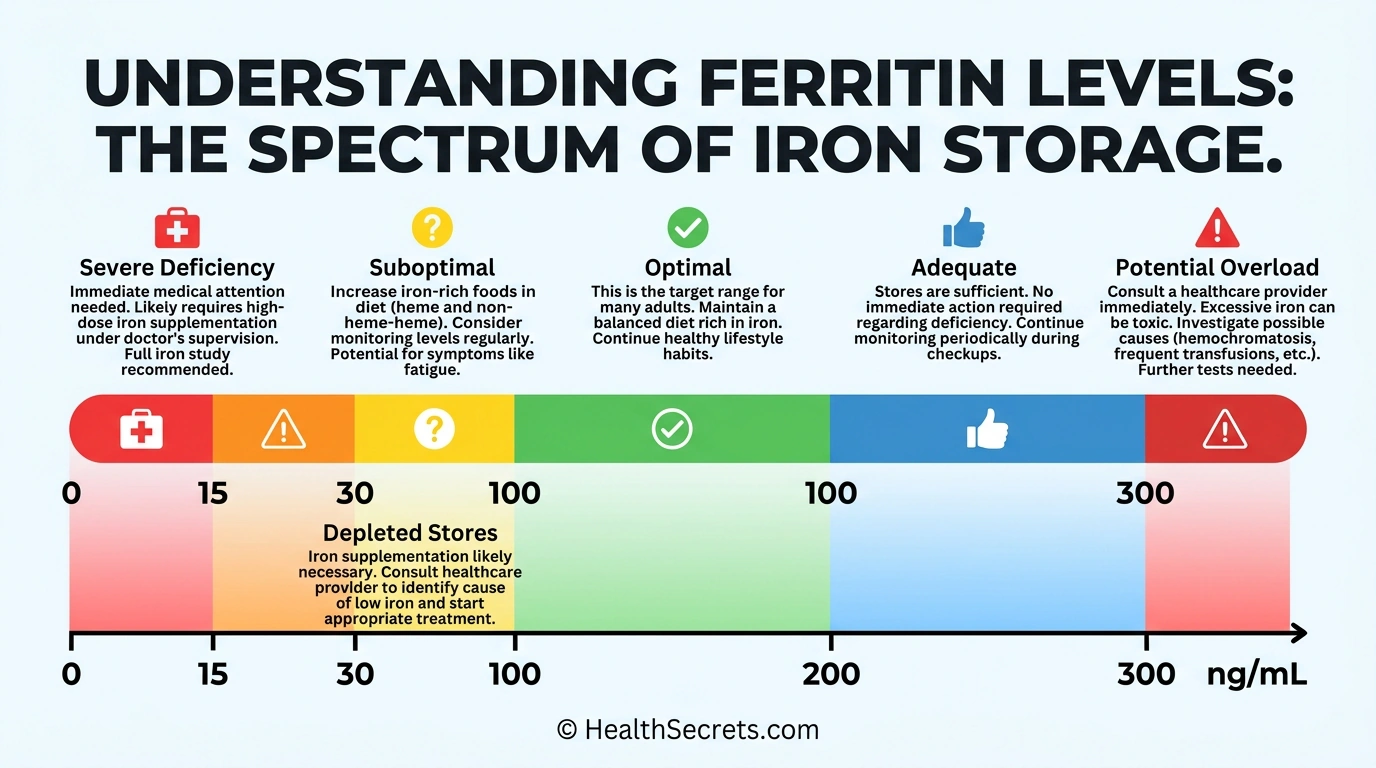
- Don't stop too early: Continue supplementation until ferritin reaches >50 ng/mL, even if hemoglobin normalizes first — stores take longer to replenish
Can You Get Enough Iron from Food Alone?
For many people with adequate iron status, a well-planned diet provides sufficient iron — but for those with increased needs or existing deficiency, food alone often falls short. The key difference lies in absorption: heme iron from animal sources is absorbed at 15–35% regardless of other dietary factors, while non-heme iron from plants absorbs at just 2–20% and is heavily influenced by enhancers and inhibitors.
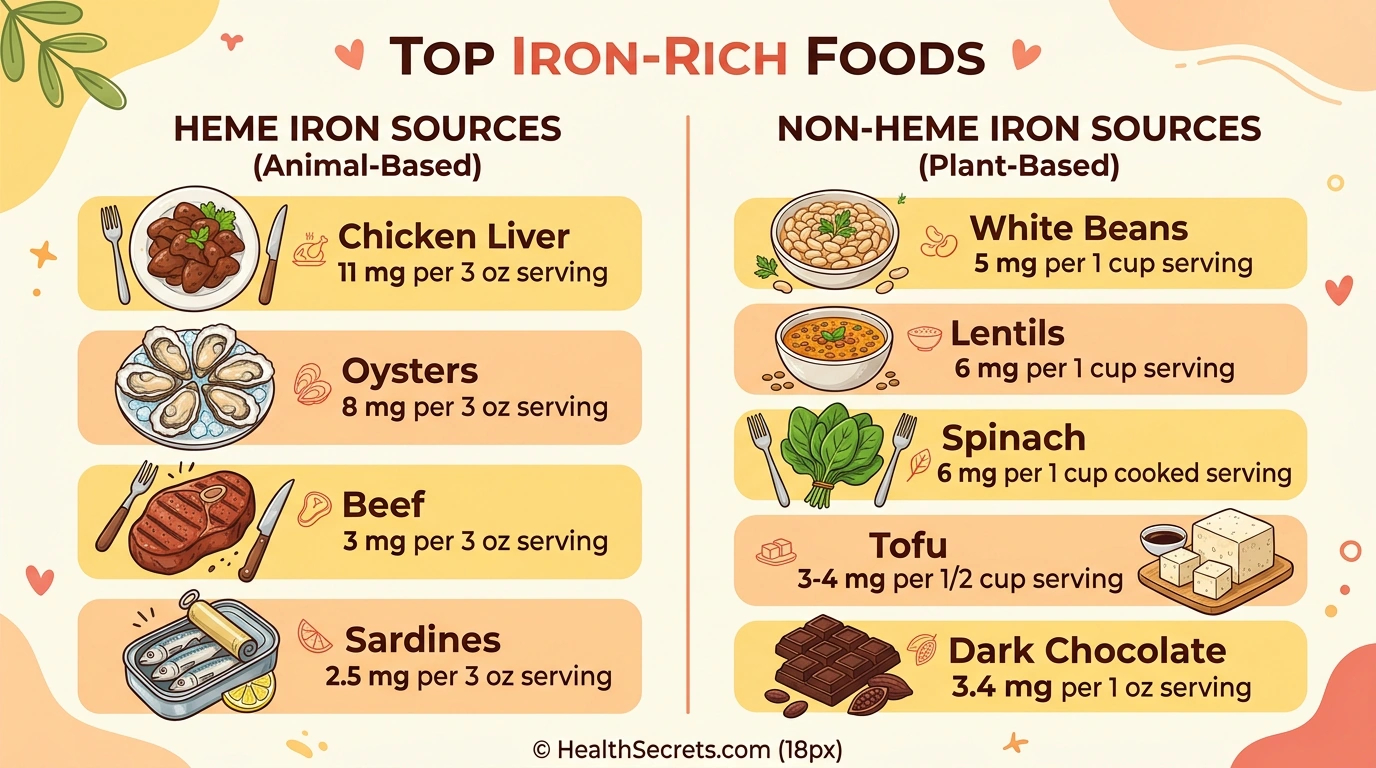
Top iron-rich foods:
| Food | Serving | Iron (mg) | % DV (women) | Type |
|---|---|---|---|---|
| Chicken liver | 3 oz | 11.0 | 61% | Heme |
| Oysters | 3 oz | 8.0 | 44% | Heme |
| White beans | 1 cup | 8.0 | 44% | Non-heme |
| Lentils (cooked) | 1 cup | 6.6 | 37% | Non-heme |
| Spinach (cooked) | 1 cup | 6.4 | 36% | Non-heme |
| Practical tips for boosting dietary iron: Pair plant-based iron sources with vitamin C-rich foods like citrus, bell peppers, or tomatoes. Cook in cast iron cookware — studies show this can increase iron content of acidic foods significantly. Soak legumes and grains before cooking to reduce phytate content and improve mineral availability. Avoid drinking tea or coffee with iron-rich meals. |
For vegetarians, vegans, menstruating women with heavy periods, and athletes — food alone may not be enough to maintain optimal ferritin levels (>50 ng/mL), and targeted supplementation becomes necessary.
Is Iron Supplementation Safe?
Iron supplementation is generally safe when taken at appropriate doses based on confirmed deficiency, but it carries unique risks compared to most supplements because the body lacks an active excretion mechanism for excess iron. This makes testing essential before and during supplementation.
Common side effects and management:
- Constipation (most common): Increase water and fiber intake, consider adding magnesium (300–400 mg has a natural laxative effect), or switch to bisglycinate
- Nausea and stomach upset: Take with a small amount of food, reduce dose, or switch to bisglycinate
- Dark/black stools: Normal and harmless — simply unabsorbed iron. Not to be confused with GI bleeding
- Metallic taste: Switch to bisglycinate (neutral taste) or take with juice
Serious risks:
- Iron overload (hemochromatosis): Genetic condition affecting ~1 in 200 people of Northern European descent. Excess iron deposits in organs causing liver damage, joint pain, diabetes, and heart problems.
Never supplement without testing.
- Acute toxicity: Doses >20 mg/kg body weight can be fatal, especially in children. Keep all iron supplements in child-proof containers and out of reach.
- Drug interactions: Iron reduces absorption of thyroid medications (levothyroxine), certain antibiotics (tetracyclines, fluoroquinolones), and Parkinson's medications (levodopa). Separate by at least 2 hours.
Who should NOT supplement iron without medical guidance:
- Men (low deficiency risk, higher overload risk)
- Postmenopausal women (reduced needs)
- Anyone with hemochromatosis or a family history
- People with chronic infections (iron can feed pathogens)
- Those with inflammatory conditions (ferritin may be falsely elevated)
What Can Iron Supplements Actually Do for You?
Iron supplementation is highly effective for correcting confirmed deficiency and anemia — but setting realistic expectations about timeline, limitations, and individual variation helps you stay consistent and avoid frustration.
Realistic timeline:
- 1–2 weeks: Some people notice improved energy, especially if severely deficient
- 4–8 weeks: Hemoglobin levels typically begin rising (expect ~1–2 g/dL increase)
- 3 months: Significant improvement in hemoglobin; retest ferritin and adjust dose
- 3–6 months: Full iron store repletion (ferritin >50 ng/mL) — this is when you can consider reducing or stopping
- 6–12 months: Some people with severe depletion or ongoing losses need longer supplementation
What iron supplements will NOT do:
- Boost energy if you're not actually iron deficient (fatigue has many causes)
- Work immediately — iron repletion is a gradual process
- Replace the need to address underlying causes (heavy periods, GI bleeding, malabsorption)
- Compensate for a very poor diet long-term without dietary improvements
Individual variation matters: Absorption varies significantly based on your current iron status (depleted bodies absorb more), gut health, concurrent medications, and genetics. If oral supplementation fails to raise ferritin after 3 months of consistent use, discuss IV iron with your healthcare provider — conditions like celiac disease, inflammatory bowel disease, or H. pylori infection may impair oral absorption.
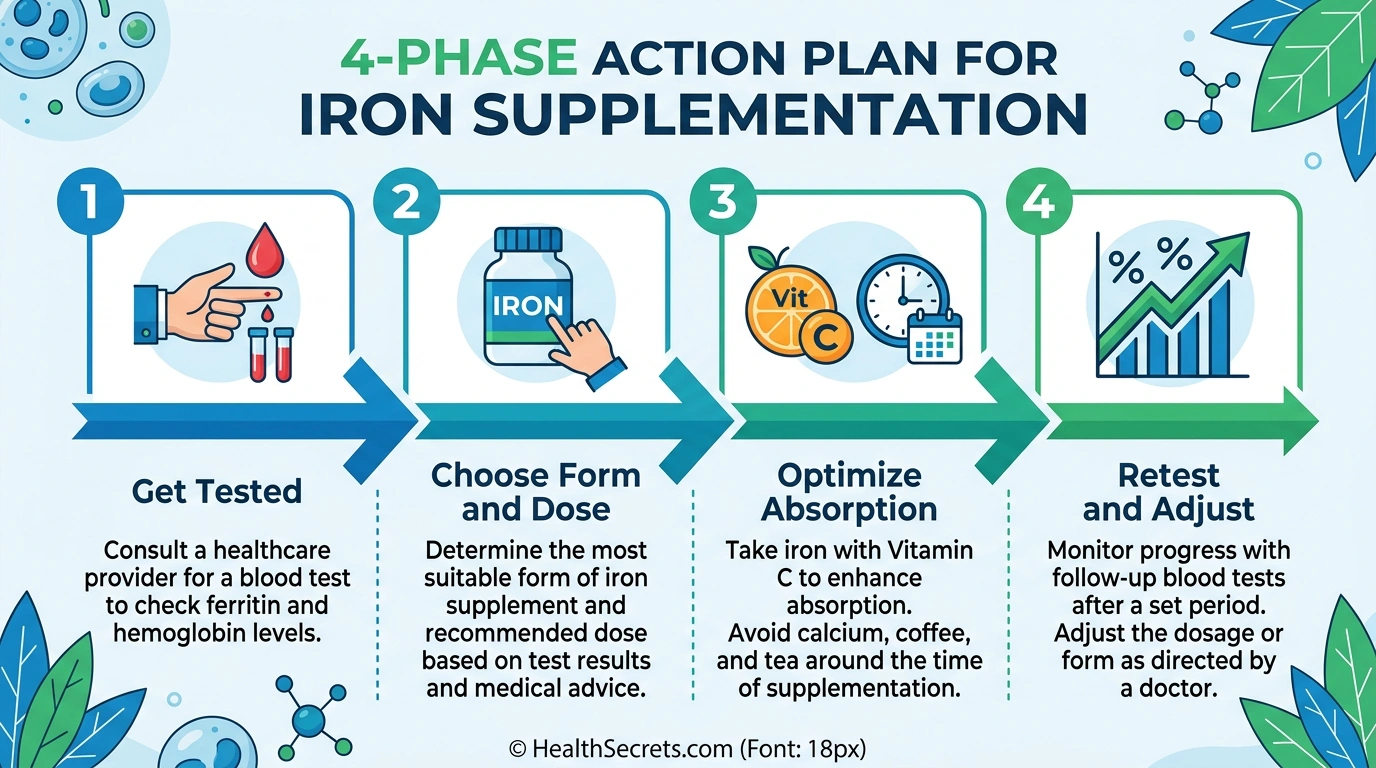
What Should You Do First if You Suspect Iron Deficiency?
If you're experiencing fatigue, brain fog, hair loss, or other deficiency symptoms, following a systematic approach ensures safe and effective iron repletion. Never start iron supplementation without first confirming deficiency through blood testing.
Phase 1 — Get Tested (Week 1):
- Request a complete iron panel: ferritin, serum iron, TIBC, transferrin saturation, hemoglobin/CBC
- Ferritin is the single most important marker — optimal is 50–100 ng/mL
- Note: ferritin can be falsely elevated by inflammation or infection
Phase 2 — Choose Your Form and Dose (Week 1–2):
- First choice: ferrous bisglycinate 25–50 mg elemental iron (best tolerated)
- Budget option: ferrous sulfate 325 mg (65 mg elemental iron)
- Purchase vitamin C (100–200 mg) to take alongside iron
- Set a consistent schedule — morning on empty stomach or with light meal
Phase 3 — Optimize and Manage (Weeks 2–12):
- Take iron with vitamin C, away from calcium, tea, and coffee
- Consider alternate-day dosing for better absorption and fewer side effects
- Address constipation early: hydration, fiber, magnesium if needed
- Track symptoms weekly to gauge improvement
Phase 4 — Retest and Adjust (Month 3):
- Recheck ferritin, hemoglobin, and complete iron panel
- If ferritin rising: continue until >50 ng/mL, then reassess
- If no improvement: consult healthcare provider about dose adjustment, form change, or IV iron
- Continue supplementation 3–6 months after hemoglobin normalizes to fully replenish stores

Thorne Iron Bisglycinate
Editor's ChoiceThorne Iron · Overall best iron supplement — excellent absorption with minimal side effects

Nature Made Iron 65 mg
Best BudgetNature Made · Affordable, effective iron for confirmed deficiency or anemia

Solgar Gentle Iron 25 mg
Best Gentle IronSolgar Gentle · Sensitive stomachs and those who failed ferrous sulfate due to GI issues

MegaFood Blood Builder
Best Iron + Vitamin C CombinationMegaFood Blood · Comprehensive iron support with built-in absorption enhancers

Flora Floradix Liquid Iron + Herbs
Best Liquid IronFlora Floradix · People who cannot swallow pills or prefer liquid supplementation

Garden of Life Vitamin Code Raw Iron
Best Whole Food IronGarden of · Those preferring whole-food-based supplements with comprehensive nutrient support

NOW Foods Iron 36 mg Double Strength
Best Value BisglycinateNOW Foods · Higher-dose bisglycinate at an affordable price point

Vitron-C High Potency Iron + Vitamin C
Best Iron + C Combo (Budget)Vitron-C High · Convenient iron plus vitamin C in a single, affordable tablet
Three Arrows Heme Iron Supplement
Best Heme IronThree Arrows · Maximum absorption without dietary inhibitor concerns
কোনো রিটেইল লিঙ্ক খোলার আগে নিচের বিস্তারিত রিভিউ কার্ডগুলো পড়ুন
উপরে প্রস্তাবিত পণ্য
Thorne Iron
Thorne Iron Bisglycinate
Thorne's iron bisglycinate delivers the most well-tolerated form of supplemental iron with excellent absorption, backed by NSF certification that guarantees purity and potency — ideal for long-term supplementation.
সুবিধা
- + Best-in-class tolerability
- + NSF Certified for Sport
- + no common allergens
- + well-researched form
অসুবিধা
- - Lower elemental iron per capsule (may need 2 for severe deficiency)
- - premium price vs ferrous sulfate
কেন আমরা এটি অন্তর্ভুক্ত করেছি: Thorne's iron bisglycinate delivers the most well-tolerated form of supplemental iron with excellent absorption, backed by NSF certification that guarantees purity and potency — ideal for long-term supplementation.
রিটেইলার লিঙ্কটি উপরের পর্যালোচনার বিস্তারিত বিবরণ দেখার পর Amazon-এ ওপেন হবে
Nature Made
Nature Made Iron 65 mg
Nature Made's USP-verified ferrous sulfate is the gold standard for treating iron deficiency anemia on a budget — the same form used in most clinical trials demonstrating efficacy.
সুবিধা
- + USP Verified for purity and potency
- + lowest cost per dose
- + high elemental iron
- + most studied form
অসুবিধা
- - Higher GI side effect risk (constipation
- - nausea)
- - may need to take with food
- - metallic taste possible
কেন আমরা এটি অন্তর্ভুক্ত করেছি: Nature Made's USP-verified ferrous sulfate is the gold standard for treating iron deficiency anemia on a budget — the same form used in most clinical trials demonstrating efficacy.
রিটেইলার লিঙ্কটি উপরের পর্যালোচনার বিস্তারিত বিবরণ দেখার পর Amazon-এ ওপেন হবে
Solgar Gentle
Solgar Gentle Iron 25 mg
Solgar Gentle Iron is specifically formulated for people who experience constipation, nausea, or stomach upset from traditional iron supplements — the bisglycinate chelate form virtually eliminates GI complaints.
সুবিধা
- + Extremely gentle on stomach
- + suitable for vegetarians
- + multiple certifications
- + no metallic taste
অসুবিধা
- - Lower dose requires 2 capsules for higher needs
- - slightly more expensive than sulfate
কেন আমরা এটি অন্তর্ভুক্ত করেছি: Solgar Gentle Iron is specifically formulated for people who experience constipation, nausea, or stomach upset from traditional iron supplements — the bisglycinate chelate form virtually eliminates GI complaints.
রিটেইলার লিঙ্কটি উপরের পর্যালোচনার বিস্তারিত বিবরণ দেখার পর Amazon-এ ওপেন হবে
MegaFood Blood
MegaFood Blood Builder
MegaFood Blood Builder is clinically shown to increase iron levels without common side effects, combining iron bisglycinate with synergistic nutrients (folate, B12, vitamin C) for a complete blood-building formula.
সুবিধা
- + Clinically studied formula
- + includes vitamin C
- + folate
- + and B12 for comprehensive blood building
- + gentle
- + vegan
অসুবিধা
- - Premium pricing
- - lower vitamin C than ideal (consider adding more)
- - larger tablet size
কেন আমরা এটি অন্তর্ভুক্ত করেছি: MegaFood Blood Builder is clinically shown to increase iron levels without common side effects, combining iron bisglycinate with synergistic nutrients (folate, B12, vitamin C) for a complete blood-building formula.
রিটেইলার লিঙ্কটি উপরের পর্যালোচনার বিস্তারিত বিবরণ দেখার পর Amazon-এ ওপেন হবে
Flora Floradix
Flora Floradix Liquid Iron + Herbs
Floradix has been the world's bestselling liquid iron supplement for decades, combining gentle ferrous gluconate with vitamin C and herbal extracts in a format ideal for those who struggle with capsules or tablets.
সুবিধা
- + Easy to absorb liquid form
- + includes vitamin C and B vitamins
- + pleasant taste
- + gentle on stomach
অসুবিধা
- - Must be refrigerated after opening
- - lower iron per dose (10 mg)
- - shorter shelf life
- - higher cost per mg
কেন আমরা এটি অন্তর্ভুক্ত করেছি: Floradix has been the world's bestselling liquid iron supplement for decades, combining gentle ferrous gluconate with vitamin C and herbal extracts in a format ideal for those who struggle with capsules or tablets.
রিটেইলার লিঙ্কটি উপরের পর্যালোচনার বিস্তারিত বিবরণ দেখার পর Amazon-এ ওপেন হবে
Garden of
Garden of Life Vitamin Code Raw Iron
Garden of Life combines whole-food iron with probiotics and digestive enzymes, making it an excellent choice for those who want comprehensive nutritional support and gentle digestion alongside iron repletion.
সুবিধা
- + Whole food nutrients
- + includes probiotics for GI support
- + gentle
- + vegan
- + comprehensive formula
অসুবিধা
- - Only 30 capsules per bottle
- - premium price per serving
- - lower iron dose for severe deficiency
কেন আমরা এটি অন্তর্ভুক্ত করেছি: Garden of Life combines whole-food iron with probiotics and digestive enzymes, making it an excellent choice for those who want comprehensive nutritional support and gentle digestion alongside iron repletion.
রিটেইলার লিঙ্কটি উপরের পর্যালোচনার বিস্তারিত বিবরণ দেখার পর Amazon-এ ওপেন হবে
NOW Foods
NOW Foods Iron 36 mg Double Strength
NOW Foods delivers a higher-dose bisglycinate using the patented Ferrochel chelate from Albion Minerals at a fraction of premium brand pricing — excellent value for those needing more than 25 mg per dose.
সুবিধা
- + Higher dose bisglycinate (36 mg) at competitive price
- + Ferrochel branded chelate
- + gentle
- + vegan
অসুবিধা
- - May be more than needed for prevention
- - no added vitamin C (take separately)
কেন আমরা এটি অন্তর্ভুক্ত করেছি: NOW Foods delivers a higher-dose bisglycinate using the patented Ferrochel chelate from Albion Minerals at a fraction of premium brand pricing — excellent value for those needing more than 25 mg per dose.
রিটেইলার লিঙ্কটি উপরের পর্যালোচনার বিস্তারিত বিবরণ দেখার পর Amazon-এ ওপেন হবে
Vitron-C High
Vitron-C High Potency Iron + Vitamin C
Vitron-C combines the safety advantages of carbonyl iron with built-in vitamin C for absorption enhancement — a smart budget pick, especially for households with children where accidental ingestion safety matters.
সুবিধা
- + Built-in vitamin C for enhanced absorption
- + carbonyl iron is safer in accidental overdose
- + affordable
অসুবিধা
- - Carbonyl iron absorbs more slowly than ferrous forms
- - may need longer supplementation
- - fewer third-party certs
কেন আমরা এটি অন্তর্ভুক্ত করেছি: Vitron-C combines the safety advantages of carbonyl iron with built-in vitamin C for absorption enhancement — a smart budget pick, especially for households with children where accidental ingestion safety matters.
রিটেইলার লিঙ্কটি উপরের পর্যালোচনার বিস্তারিত বিবরণ দেখার পর Amazon-এ ওপেন হবে
Three Arrows
Three Arrows Heme Iron Supplement
Heme iron polypeptide mimics the highly bioavailable iron found naturally in meat, absorbing through a separate pathway unaffected by common dietary inhibitors — ideal for those who need maximum absorption.
সুবিধা
- + Highest bioavailability (15–35% absorption)
- + not affected by calcium
- + tea
- + or phytates
- + minimal GI side effects
অসুবিধা
- - Animal-derived (not for vegetarians/vegans)
- - premium pricing
- - lower elemental iron per capsule
- - limited availability
কেন আমরা এটি অন্তর্ভুক্ত করেছি: Heme iron polypeptide mimics the highly bioavailable iron found naturally in meat, absorbing through a separate pathway unaffected by common dietary inhibitors — ideal for those who need maximum absorption.
রিটেইলার লিঙ্কটি উপরের পর্যালোচনার বিস্তারিত বিবরণ দেখার পর Amazon-এ ওপেন হবে
আরও পড়ুন
আরও পড়ুন
"Cure Your Fatigue: Get Your Life Back with the 4-Phase Approach"
দ্বারা Morley Robbins
Comprehensive framework for understanding iron dysregulation; practical protocols for restoring mineral balance; evidence-based approach to fatigue beyond simple iron supplementation
এটি কেন এখানে গুরুত্বপূর্ণ
Robbins challenges conventional iron supplementation dogma by exploring the critical iron-copper relationship and why blindly adding iron without addressing root causes can backfire.
সেরা উপযোগী: Anyone wanting a deep dive into iron metabolism, copper interactions, and the Root Cause Protocol
বইয়ের বিস্তারিত দেখুনআরও পড়ুন
"Iron Deficiency and Overload: From Biology to Clinical Medicine"
দ্বারা Stig Borgström and Lars Hallberg (Editors)
Comprehensive clinical reference on iron metabolism; diagnostic algorithms; treatment protocols for deficiency and overload; latest research summaries
এটি কেন এখানে গুরুত্বপূর্ণ
This clinical reference bridges the gap between basic iron science and practical treatment decision-making, covering everything from ferritin interpretation to IV iron protocols.
সেরা উপযোগী: Healthcare professionals and advanced readers wanting clinical-depth iron science
বইয়ের বিস্তারিত দেখুনAEO FAQ
সচরাচর জিজ্ঞাসিত প্রশ্নাবলী
12 common questions answered
Iron absorbs 2–3 times better on an empty stomach (1 hour before or 2 hours after meals). However, if you experience nausea or stomach upset, take iron with a small, low-calcium meal — reduced absorption is better than not taking it at all. Always pair with vitamin C regardless of timing.
Most people notice energy improvements within 2–4 weeks, with hemoglobin levels rising within 4–8 weeks. Full iron store repletion (ferritin >50 ng/mL) typically requires 3–6 months of consistent supplementation. Don't stop when you feel better — continue until blood tests confirm adequate stores.
Iron slows gut motility and can harden stool, especially ferrous sulfate at doses above 45 mg. To prevent constipation: switch to ferrous bisglycinate (much gentler), increase water intake to 8–10 glasses daily, add fiber-rich foods, exercise regularly, or add a magnesium supplement (300–400 mg) which has a natural laxative effect.
For most people, yes. Research shows bisglycinate achieves comparable absorption to ferrous sulfate with significantly fewer GI side effects. A randomized trial found 25 mg bisglycinate was as effective as 50 mg ferrous sulfate for preventing iron deficiency during pregnancy. Ferrous sulfate remains appropriate for severe anemia on a tight budget.
No — calcium strongly inhibits iron absorption by competing for the same transport mechanisms. Separate iron and calcium supplements (including dairy products) by at least 2 hours. Take iron in the morning and calcium in the evening, or vice versa, to maximize absorption of both minerals.
A ferritin level below 30 ng/mL indicates depleted iron stores and warrants supplementation. Many experts now consider levels below 50 ng/mL suboptimal, especially if symptoms like fatigue, brain fog, or hair loss are present. Optimal ferritin for most people is 50–100 ng/mL. Always confirm with a complete iron panel.
Yes — iron supplementation during pregnancy is recommended by major health organizations because blood volume increases by 50% and the fetus requires significant iron for development. The RDA increases from 18 mg to 27 mg daily during pregnancy. Ferrous bisglycinate is preferred for better tolerability. Always take under prenatal care guidance.
Yes — excess iron is toxic because the body has no active excretion mechanism. Iron overload causes oxidative damage to the liver, heart, and pancreas. Acute iron poisoning (>20 mg/kg body weight) can be fatal, especially in children. Never supplement iron without confirmed deficiency through blood testing, and keep supplements away from children.
Dark green or black stools are a harmless and expected side effect of iron supplementation — they're caused by unabsorbed iron passing through the digestive tract. This is not a sign of GI bleeding. However, if you notice black, tarry stools with a foul odor before starting iron, or if you experience stomach pain, consult your doctor.
Recent research from ETH Zurich suggests alternate-day dosing may be more effective than daily dosing. Oral iron triggers a hepcidin spike that suppresses absorption for 24 hours, making the next day's dose less effective. Alternate-day dosing showed 33% higher fractional iron absorption. Discuss this approach with your healthcare provider.
Not necessarily, but they're at higher risk for deficiency because plant-based (non-heme) iron absorbs at only 2–20% compared to 15–35% for heme iron from meat. Vegetarians need approximately 1.8 times more dietary iron. If ferritin is below 50 ng/mL or symptoms are present, supplementation is recommended — bisglycinate is an effective vegan-friendly form.
You should avoid coffee and tea within 1–2 hours of taking iron supplements. Tannins in tea and polyphenols in coffee bind to iron and can reduce absorption by 50–90%. If you drink coffee in the morning, take your iron supplement at least 2 hours later, or switch to evening dosing away from caffeinated beverages.
Evidence-Based Supplement Organizer & Safety Log
Track your daily intake, verify third-party certifications, and prepare clear questions for your clinician.
What's Inside This Complete Digital System:
Instant PDF download • Lifetime updates • 60-day money-back guarantee
আপনার জ্ঞান যাচাই করুন
Take our Supplement Science Quiz and see how much you really know about supplements.
এই নিবন্ধটি কি সহায়ক ছিল?
গবেষিত ও তথ্য-যাচাইকৃত
লেখক
Health Secrets Editorial TeamThe Health Secrets editorial team researches, writes and fact-checks every guide against the primary studies and clinical guidelines it cites.
তথ্য-যাচাইকারী
Health Secrets Editorial Teamসব বিষয়বস্তু প্রমাণ-ভিত্তিক, পিয়ার-রিভিউড গবেষণার সঙ্গে যাচাইকৃত এবং নিয়মিত হালনাগাদ করা হয়। আমাদের সম্পাদকীয় দল নির্ভুলতা ও স্বচ্ছতার কঠোর নির্দেশিকা অনুসরণ করে।
রেফারেন্স ও উদ্ধৃতি
20 উৎস উদ্ধৃত
চিকিৎসাগত সতর্কবার্তা
This article is for informational purposes only and does not constitute medical advice. Read the full medical disclaimer. Always consult with a qualified healthcare provider before starting any new supplement, treatment, or major dietary change.
The Complete Guide to Supplements
Explore our foundational comprehensive guide covering all clinical protocols, dietary strategies, and evidence for supplements.
আপনি যা পছন্দ করতে পারেন
Supplements for Energy: Combat Fatigue Naturally
Supplements for energy can help combat persistent fatigue when the right ones target your specific deficiency. B vitamins, iron, CoQ10, magnesium, and adaptogens like rhodiola are among the most evidence-backed options — but testing your levels first is critical to avoid wasting money or causing harm.
→CoQ10 Complete Guide: Cellular Energy and Heart Health
CoQ10 (coenzyme Q10) is an essential compound found in every cell that powers mitochondrial energy production and acts as a potent antioxidant. This evidence-based guide covers ubiquinol vs ubiquinone, cardiovascular benefits, statin-induced depletion, optimal dosing, absorption tips, and the best CoQ10 supplements for heart health and cellular energy.
→Protein Supplements: Complete Guide for Health and Fitness
Discover the best protein supplements for 2025 with our evidence-based guide. We compare whey, casein, and plant-based proteins, review the top 10 products for purity and value, and share expert tips on dosing, timing, and safety backed by peer-reviewed research.
→আলোচনা
0No comments yet
Be the first to share your thoughts, clinical insights, or questions about this protocol.